Device Overview
The Bravo™ reflux recorder is a wireless pH sensor attached to the esophageal mucosa, transmitting real‑time acidity data to a handheld recorder. It offers continuous 48‑hour monitoring, enabling clinicians to correlate reflux events with symptoms and lifestyle factors. Follow guidelines for accuracy
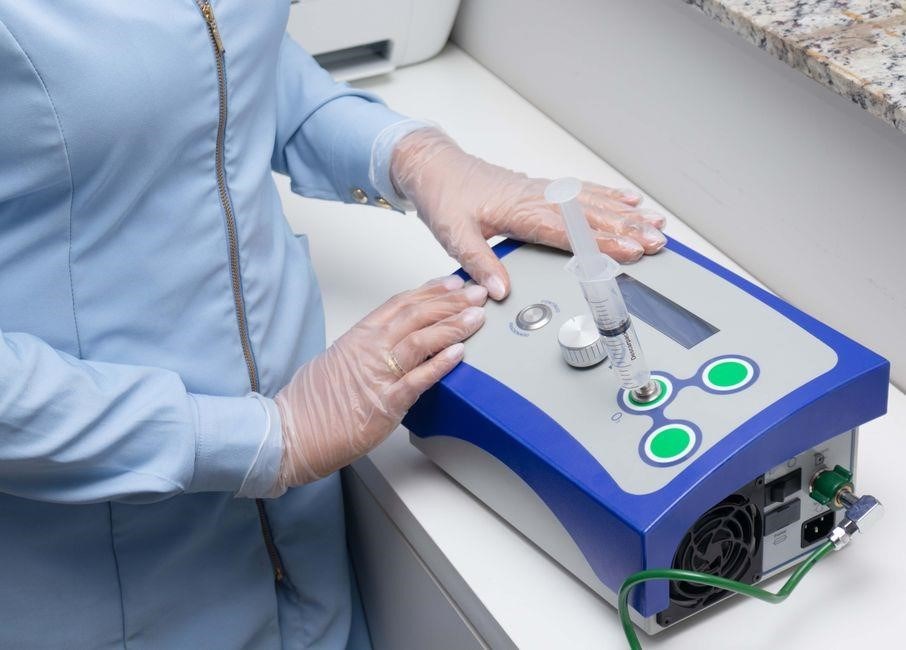
Purpose and Clinical Use
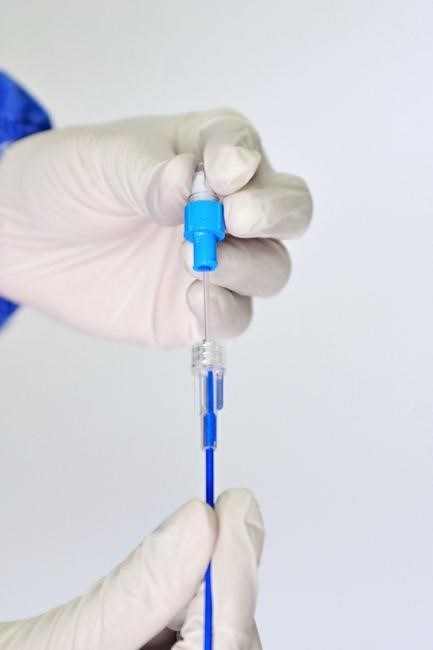
The Bravo™ reflux recorder is a minimally invasive, wireless pH monitoring system designed to objectively quantify gastroesophageal reflux episodes over a 48‑hour period. By attaching a small, disposable sensor to the esophageal lining, the device continuously measures intraluminal acidity and transmits data to a handheld recorder. Clinicians use the recorded pH curves to assess the frequency, duration, and severity of acid reflux events, correlating them with patient‑reported symptoms such as heartburn, regurgitation, chest pain, and nocturnal awakenings. This objective evidence supports diagnosis of gastroesophageal reflux disease (GERD), evaluates treatment efficacy, and guides therapeutic decisions. The system is especially valuable in patients with atypical symptoms, refractory reflux, or when empirical therapy fails, allowing tailored management plans. Proper patient education, accurate diary logging, and adherence to procedural protocols are essential to obtain reliable data and maximize diagnostic yield. The Bravo™ system thus serves as a cornerstone tool in modern reflux evaluation, bridging clinical assessment with quantitative metrics. Its indications include suspected GERD, evaluation of refractory reflux, assessment of treatment response, and pre‑operative evaluation for anti‑reflux surgery. Contraindications involve active esophageal ulceration, severe esophagitis, or recent upper GI surgery. The sensor attaches via a small balloon that inflates to secure contact, and the recorder is worn on the chest, providing continuous wireless data transmission. The system’s ability to capture nocturnal reflux and correlate it with sleep patterns offers unique insights into disease burden and quality of life. By integrating patient diaries with objective pH data, clinicians can tailor pharmacologic therapy, lifestyle modifications, and surgical referrals with greater precision!!!

Key Components and Sensors
The Bravo™ system comprises a disposable, 1.5‑mm diameter pH sensor that attaches to the esophageal mucosa via a small balloon. The sensor contains a glass electrode calibrated to detect pH values from 0 to 7, with a sensitivity of 0.1 pH units. A miniature radio‑frequency transmitter embedded in the sensor wirelessly relays real‑time acidity data to a handheld recorder worn on the patient’s chest. The recorder houses a rechargeable lithium‑ion battery that supports up to 48 hours of continuous operation, a micro‑controller for data logging, and a built‑in display that shows current pH, time, and event markers. The recorder’s antenna receives signals from the sensor and stores them in internal flash memory, which can be downloaded via a USB interface or transmitted to a cloud‑based platform for analysis. The sensor’s balloon is inflated with a sterile saline solution to secure mucosal contact; the balloon’s volume is calibrated to maintain a constant pressure of approximately 2 mmHg, ensuring optimal signal quality while minimizing tissue irritation. The adhesive backing on the recorder provides secure attachment to the skin, and the device includes a battery indicator and a low‑power mode that conserves energy during periods of inactivity. Together, these components deliver a reliable, patient‑friendly method for quantifying acid reflux events over a 48‑hour period, enabling clinicians to correlate objective data with patient diaries and symptom reports. All components are sterilized!
Technical Principles of Acid Detection
The Bravo™ system employs a glass‑electrode pH sensor that measures the hydrogen ion concentration in the esophageal lumen. The electrode is coated with a selective membrane that permits H+ ions to pass while blocking larger molecules, allowing the sensor to generate a voltage proportional to the pH. This voltage is amplified and digitized by the sensor’s onboard circuitry, then transmitted via a low‑frequency radio link to the external recorder. The recorder’s microcontroller samples the incoming signal at a fixed rate (typically 1 Hz), applies a calibration curve derived from a standard pH buffer, and converts the digital value into a pH reading displayed in real time. The system uses a 48‑hour battery‑powered transmitter that maintains a stable carrier frequency (≈ 433 MHz) to avoid interference with other medical devices. Data are stored in non‑volatile memory and can be downloaded for analysis. The sensor’s balloon ensures close mucosal contact, reducing signal drift caused by movement or saliva. The entire detection chain—from ion‑selective membrane to wireless transmission—provides continuous, accurate monitoring of acid reflux events, enabling correlation with patient‑reported symptoms and lifestyle factors. This technology allows clinicians to objectively assess reflux severity and treatment efficacy.The system’s robust design, low power consumption, and user-friendly interface make it a reliable tool for both patients and clinicians seeking precise reflux monitoring!!

Setup and Insertion
Patient preparation includes fasting, medication review, and informed consent. The recorder is attached to the esophagus via a balloon that inflates with saline, securing the sensor to mucosa. After placement, the recorder is activated, and data logging begins immediately and check battery status!
Patient Preparation and Consent

Before the Bravo™ system is applied, patients must undergo a thorough preparation protocol to ensure accurate data collection and minimize procedural risks. The first step is a detailed medical history review, focusing on previous reflux episodes, current medications, and any contraindications such as esophageal strictures or recent abdominal surgery. Patients should be instructed to discontinue proton‑pump inhibitors, H2 blockers, antacids, and other acid‑reducing agents for at least 48 hours prior to the test, unless a physician specifically advises otherwise. Fasting for a minimum of 6 hours before the procedure is mandatory to reduce gastric volume and lower the likelihood of aspiration during balloon inflation.
During the consent discussion, clinicians explain the test purpose, insertion method, potential discomfort, and risk of mild bleeding or chest pain. Patients learn the sensor stays attached for the recording period and that data is transmitted wirelessly to a handheld unit. Consent covers privacy, data handling, and withdrawal rights.
On the procedure day, patients arrive with a brief explanation of steps: catheter insertion, balloon inflation to secure the sensor, and recorder attachment to the skin. The clinician verifies identity, fasting status, and medication list before proceeding.
After placement, the recorder activates and the patient receives a diary to log meals, sleep, and symptoms. Of events; patients record exact times as shown on the recorder, ensuring reliable data.now
Recorder Placement Procedure

After the patient has been fully informed and has signed the consent form, the clinician begins the placement of the Bravo™ recorder. The procedure is performed in a clean, well‑lit area with the patient lying supine. A sterile, disposable catheter with a 3‑mm balloon is introduced orally and advanced under direct visualization or by gentle guidance to the distal esophagus, just above the gastroesophageal junction. The balloon is inflated with 1.5 mL of sterile saline, ensuring it is fully seated against the mucosa. The catheter is then gently withdrawn, leaving the balloon attached to the esophageal wall. The recorder, a small, lightweight unit, is clipped to the patient’s chest over the left mid‑sternal area, where it receives the wireless signal from the balloon. The recorder’s adhesive patch is secured with a hypoallergenic tape to prevent dislodgement during the 48‑hour monitoring period. The clinician checks the signal strength on the recorder’s display, confirming a stable transmission. The patient is instructed to keep the recorder in place, avoid excessive movement, and to keep the diary for event logging. The entire process takes approximately 5–10 minutes and is performed with minimal discomfort. Proper placement is critical for accurate pH measurement and reliable data capture throughout the study period.
Clinicians verify the recorder’s battery and synchronize it with diary software. The patient learns to use buttons for meals, lying periods, and symptoms, recording times as shown. After placement, monitoring for chest discomfort or swallowing difficulty occurs, and the procedure is logged!!

Verification of Sensor Functionality
After the Bravo™ recorder is attached, the clinician confirms wireless transmission and calibrates the pH sensor. The display shows a steady “pH” reading within the expected range (4–7) when the patient is upright. A 30‑second calibration check is performed by pressing the “Calibrate” button; the screen should display “Cal” and the baseline pH is recorded. The clinician then asks the patient to swallow a sip of water; a rapid dip confirms sensor responsiveness. If the display shows a flat line or erratic values, the sensor may be mis‑mounted or the balloon shifted; the recorder is removed, the balloon re‑inflated, and the sensor repositioned. Once a stable baseline is achieved, the clinician records the verification time in the diary and instructs the patient to keep the recorder on for 48 hours. Regular checks at 12‑hour intervals ensure signal integrity, especially if the patient reports discomfort or the battery indicator is low. Proper verification guarantees accurate reflux data and reliable analysis. The clinician also verifies battery level above 80 % before the patient leaves, ensures the adhesive patch is intact, and confirms the recorder’s internal clock matches the patient’s local time zone. Finally, the clinician reviews the first 10‑minute recording segment, confirming a smooth pH trend and no sudden spikes or drops without patient‑reported events. This comprehensive verification process ensures optimal sensor function and data integrity throughout the monitoring period. The patient is also instructed to record any episodes of regurgitation, or chest discomfort, noting the time and severity, to aid in correlating symptoms with pH events during analysis and

Daily Operation and Diary Maintenance
Patients log meals, sleep, and symptoms by pressing the recorder button and noting the time in the diary. They record medication use, posture changes, and any reflux events. Accurate entries enable clinicians to correlate PH data with lifestyle factors.
Recording Meals, Sleep, and Symptom Events
To capture accurate reflux data, patients must use the recorder’s buttons to log each event. Begin by pressing any button to illuminate the backlight, then press the designated button for the event type. Record the exact time shown on the display and write it in the diary next to the event description.
Meals: Press the “Meal” button at the start and again at the end of each meal. Note the duration and any reflux symptoms that arise during or after eating.
Sleep: When lying down for sleep, press the “Sleep” button at bedtime and again upon waking. This records posture changes that influence reflux.
Symptoms: For heartburn, regurgitation, or chest discomfort, press the “Symptom” button each time it occurs. Include a brief note on severity and any triggers.
Medication: Log any antacid or acid‑suppression drug taken by pressing the “Med” button and noting the time. This helps differentiate drug‑related changes from natural reflux.
Consistency is key. Encourage patients to record events promptly and to keep the diary organized so the physician can accurately interpret the 48‑hour data set.
Patients should note any changes in body position during meals, such as sitting upright or lying down, as these can affect reflux timing. Recording the duration of each meal and the time between eating and lying down helps identify patterns. Additionally, marking any activities, like walking or exercise, provides context for symptom onset.
Diary Entry Timing and Accuracy
Accurate timing of diary entries is essential for correlating reflux events with patient activities. The recorder’s display shows the time in HH:MM format; patients should record the exact time immediately after pressing the event button. Delays of more than 5 minutes can introduce misalignment between recorded symptoms and pH data, reducing diagnostic value. To maintain precision, patients should keep a small notebook or use a digital app that syncs with the recorder’s clock. When logging meals, start and end times should be noted within 2 minutes of the event. For sleep periods, the bedtime and wake‑up times must be entered as soon as the patient lies down or stands up, respectively. Symptom entries should include a brief description and severity rating; this helps the clinician assess the clinical significance of each event. Consistency in entry timing also aids in identifying circadian patterns of reflux. Patients should be instructed to avoid writing entries after the 48‑hour monitoring period, as this data will not be transmitted. The recorder’s battery life and data storage capacity are sufficient for continuous monitoring, but any interruption in logging can create gaps. Therefore, patients should review the diary daily, ensuring that all entries are complete and accurately timestamped. Regular reminders and check‑ins with the clinical team can reinforce good logging habits and improve overall study quality. Patients should review their diary entries daily to ensure completeness accuracy.
Medication and Lifestyle Logging
Patients must record every medication taken during the 48‑hour monitoring period, including over‑the‑counter antacids, proton‑pump inhibitors, H2 blockers, and any supplements that may influence esophageal pH. Each entry should include the drug name, dosage, and exact time of ingestion, as the recorder’s clock is the reference for correlating drug effects with reflux events. For medications that require multiple daily doses, patients should log each dose separately, noting whether it was taken with food or on an empty stomach, since this can alter absorption and reflux risk. Lifestyle factors such as meal composition, portion size, and eating speed should also be recorded. Patients should note whether meals were eaten quickly or slowly, and whether they included high‑fat, spicy, or acidic foods, all of which can precipitate reflux. Post‑meal positioning is critical; patients should log whether they remained upright, reclined, or engaged in physical activity within the first 30 minutes after eating. Sleep habits, including bedtime, wake time, and any nighttime awakenings, should be documented, as nocturnal reflux is common. Additionally, patients should log alcohol episodes, daily smoking, or caffeine intake, specifying quantity and timing. This comprehensive logging allows clinicians to identify patterns linking medication timing and lifestyle to reflux severity; Review of the diary with the clinician, can help refine schedules or suggest changes that may reduce reflux episodes and improve outcomes.
Data Retrieval, Analysis, and Reporting
After the 48‑hour study, the recorder is removed and data are uploaded via the Bravo software. The program aligns pH traces with diary entries, calculates reflux metrics, and generates a PDF report for the clinician. The report links symptoms to H events
Uploading Study to the Bravo System
Once the recorder is removed, connect it to the computer using the supplied USB cable. Launch the Bravo software and select “Import Study.” The program will detect the recorder’s serial number and prompt you to confirm the patient ID and study date. After validation, click “Start Import.” The data file, typically in .brv format, will be transferred to the local database. Next, open the “Event List” window to review the automatically generated event markers. Verify that meal, sleep, and symptom timestamps match the patient diary entries; adjust any discrepancies by dragging the event markers. Once the event list is finalized, the software will compute reflux parameters such as total acid exposure time, number of reflux episodes, and symptom‑reflux correlation indices. Finally, choose “Generate Report” to produce a PDF summary that includes the pH trace, event annotations, and statistical tables. Save the report to the patient’s electronic health record and email a copy to the referring physician if required.
The software’s graphical interface displays a time‑aligned pH trace alongside event markers. Users can zoom into specific intervals, annotate additional events, and export raw data for external analysis. If the recorder fails to connect, verify the USB port, ensure the device is powered, and retry the import. Successful uploads are confirmed by a green status icon and a summary window that lists total recording duration and any missing data segments promptly
Interpreting Reflux Events and Patterns
The Bravo™ system records continuous pH values, enabling clinicians to detect reflux episodes when the pH falls below 4 for at least 5 seconds. Episodes are automatically flagged, yet manual review remains essential to confirm true reflux versus transient acid dips. Correlate each episode with the patient’s event diary—meals, lying periods, and symptom reports—to identify triggers. A high frequency of post‑prandial reflux suggests dietary factors, while nighttime episodes point to nocturnal acid exposure. Total acid exposure time (TAET) is the percentage of the recording period with pH <4; values above 4% are generally abnormal. The reflux index (RI) counts reflux events per hour; an RI > 1.5 often warrants intervention. Symptom‑reflux correlation (SRC) assesses the proportion of symptoms occurring within a 2‑hour window after a reflux event; an SRC > 50% indicates a strong association.
Plotting the pH trace with event markers provides a visual summary: episodes cluster around meals or sleep periods, revealing patterns that guide treatment. The software’s export function generates a PDF report containing the pH curve, event list, and calculated indices, which can be shared with the treating physician for decision‑making. Continuous 48‑hour monitoring offers a robust assessment of acid exposure, reducing the need for repeated invasive tests and improving diagnostic accuracy. When interpreting data, consider artifacts such as brief signal losses that may inflate episode counts. Integrating objective metrics with subjective symptom logs yields a comprehensive view of esophageal acid exposure, enabling personalized therapy and better patient outcomes. Check the summary for keyfindings!

Generating Clinical Reports for Physicians
The Bravo™ reporting module compiles raw pH data, event logs, and calculated metrics into a single, physician‑ready PDF. After the recorder is uploaded, the software automatically segments the 48‑hour trace into daytime and nighttime windows, calculates total acid exposure time (TAET), reflux index (RI), and symptom‑reflux correlation (SRC); Each episode is annotated with start and end times, peak acidity, and associated patient‑reported events. The report includes a color‑coded pH curve, a bar graph of episode frequency per hour, and a table listing all recorded meals, sleep periods, and symptom occurrences. A summary section highlights abnormal findings: TAET > 4%, RI > 1.5, SRC > 50%, or any nighttime reflux exceeding 10% of the total exposure. The software also flags potential artifacts such as brief signal drops or sensor displacement. Clinicians can export the report to the electronic health record (EHR) or share it via secure email. Customization options allow the inclusion of patient demographics, medication lists, and prior diagnostic results. The final PDF is fully searchable, enabling quick reference to specific time points or events. By presenting objective data alongside subjective diary entries, the report facilitates evidence‑based treatment decisions and follow‑up planning.
For audit and quality assurance, the report also contains a compliance checklist that verifies sensor placement accuracy, patient adherence to diary entries, and proper signal integrity. The software’s “Event Summary” tab aggregates episodes by meal type, allowing clinicians to see whether reflux predominantly occurs after high‑fat or acidic foods. Additionally, the “Sleep Analysis” section quantifies nighttime acid exposure relative to body position, offering insights into positional reflux management. All numeric values are displayed with two decimal places for precision, and the report includes a legend explaining each metric’s clinical significance. Exported data can be imported into statistical software for further analysis, supporting research studies or longitudinal follow‑up. The user interface permits the physician to annotate specific time points directly on the pH trace, adding clinical notes that will appear in the final PDF. This level of detail ensures that the report serves as a comprehensive, evidence‑based tool for both immediate clinical decision‑making and long‑term patient care planning.
The report also provides a “Compliance Score” that evaluates patient adherence to the diary and medication schedule, giving clinicians a quick gauge of lifestyle impact on reflux control. This score is calculated by comparing logged events against expected patterns, and it is displayed prominently in the summary section. Clinicians can review this score each visit daily monitoring.